Article
Dystocia in Chelonians: Practical Decision-Making From Diagnosis to Surgical Intervention
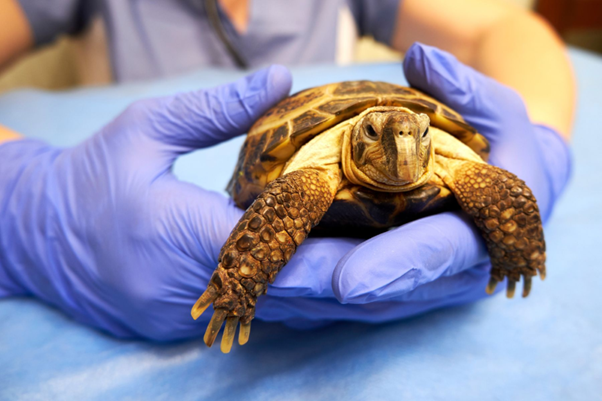
Dystocia remains one of the most clinically significant reproductive emergencies encountered in captive chelonians. Although egg retention is commonly discussed in reptile medicine, differentiating physiologic egg retention from true dystocia is often far more complicated in daily practice than textbooks suggest.
Female chelonians can naturally retain eggs for extended periods, sometimes up to six months, while waiting for optimal oviposition conditions1. This biological adaptation makes clinical judgment essential, particularly when evaluating gravid females with vague or intermittent signs.
Obstructive vs Nonobstructive Dystocia
A practical way to approach dystocia clinically is by separating cases into obstructive and nonobstructive causes1,2.
Obstructive dystocia typically involves physical inability to pass eggs. Causes may include:
- Oversized or malformed eggs
- Egg adhesions to the oviduct
- Pelvic deformities
- Oviductal stenosis
- Coelomic masses
- Constipation
- Bladder calculi
- Organomegaly or neoplasia1
Radiographically, chronically retained eggs may develop excessively mineralized or lamellar shells, a finding frequently associated with long-standing retention1,3.
Nonobstructive dystocia, on the other hand, is often heavily influenced by husbandry. Inadequate nesting sites, incorrect humidity or temperature, poor photoperiod management, malnutrition, obesity, dehydration, and chronic stress are major contributors1.
From a clinical standpoint, many nonobstructive cases can improve once environmental factors are corrected early enough.
Recognizing the Red Flags
Early dystocia may present only as restlessness and repeated unsuccessful nesting attempts1. However, advanced disease can progress rapidly into systemic compromise.
Veterinarians should be alert for:
- Anorexia
- Dehydration
- Dyspnea
- Weakness
- Hindlimb paralysis
- Cloacal bleeding
- Distended prefemoral fossae
- Malodorous cloacal discharge1
One particularly important complication is ectopic egg retention. Eggs may rupture into the coelomic cavity or migrate into the urinary bladder, colon, or surrounding tissues. Oxytocin-associated oviductal rupture and previous salpingotomy procedures have both been linked to ectopic egg formation1.
Imaging Changes Clinical Outcomes
Radiography remains the fastest first-line diagnostic tool for confirming the presence, number, and morphology of eggs. However, ultrasound and CT imaging are increasingly valuable for identifying exact egg location, associated soft tissue pathology, and concurrent complications1.
CT is especially useful in complex cases because it eliminates organ overlap and provides detailed evaluation of egg density, size, and positioning1.
Blood work is often nonspecific, although hypocalcemia, hyperuricemia, and hyperkalemia may develop in chronic or complicated cases1.
Medical Therapy Is Not Always Benign
Oxytocin therapy continues to be widely used in chelonian dystocia, but it should never be approached casually.
Successful use depends heavily on:
- Proper hydration
- Calcium supplementation
- Appropriate environmental temperature
- Availability of a nesting site1
Reported dosages vary significantly from 1–40 IU/kg depending on species and protocol1. Importantly, oxytocin carries real risks, including oviductal rupture, spasms, and ectopic egg displacement into the urinary bladder1.
For clinicians, this highlights a crucial point: oxytocin should only be used after confirming that no mechanical obstruction exists.
When Surgery Becomes Necessary
When medical therapy fails, or when obstructive disease is identified, surgery becomes unavoidable.
The prefemoral approach is increasingly preferred because it offers reduced invasiveness and shorter recovery compared with plastronotomy. However, plastronotomy remains essential in cases involving large dystocic eggs, extensive fibrosis, or inaccessible reproductive structures1,4.
Cloacal ovocentesis may provide temporary relief in selected cases, particularly when surgery is financially or medically contraindicated. Still, clinicians must recognize that this is a palliative rather than definitive procedure and may predispose patients to salpingitis or egg yolk coelomitis1.
Ultimately, successful dystocia management depends less on a single treatment protocol and more on accurate case selection, imaging-guided decision-making, and early intervention before systemic deterioration occurs.
Conclusion
Dystocia in chelonians is far more complex than simple egg retention and requires clinicians to differentiate carefully between physiologic gravidity and true reproductive pathology. Accurate diagnosis relies on a combination of thorough husbandry evaluation, clinical examination, and advanced imaging modalities.
While oxytocin therapy can be effective in selected nonobstructive cases, inappropriate use may worsen complications, including ectopic egg retention and oviductal rupture. Timely surgical intervention, guided by proper case assessment, remains critical in advanced or obstructive disease. Ultimately, successful outcomes depend on early recognition, patient stabilization, and a practical, imaging-driven treatment approach.
Reference
- Lubian E, Palotti G, Di Ianni F, Vetere A. Disorders of the female reproductive tract in chelonians: A review. Animals. 2025 Apr 30;15(9):1275. https://www.mdpi.com/2076-2615/15/9/1275
- Mans C, Foster JD. Endoscopy-guided ectopic egg removal from the urinary bladder in a leopard tortoise (Stigmochelys pardalis). The Canadian Veterinary Journal. 2014 Jun;55(6):569. https://pmc.ncbi.nlm.nih.gov/articles/PMC4022026/pdf/cvj_06_569.pdf
- Hellebuyck T, Solanes Vilanova F. The use of prefemoral endoscope-assisted surgery and transplastron coeliotomy in chelonian reproductive disorders. Animals. 2022 Dec 6;12(23):3439. https://www.mdpi.com/2076-2615/12/23/3439
- Rodrigues MC, Lima WC, Quessada AM, Silva FA, Silva LM, Souza AB, Moura CR, Lima DA. Celiotomy by plastrotomy in a yellow-footed tortoise (Geochelone denticulata). Pesquisa Veterinária Brasileira. 2015 Feb;35(2):173-6. https://www.scielo.br/j/pvb/a/pgbzsQxvFNbtFzVHSRh4HYc/?format=pdf&lang=en
Related Contents
Article
Recognising Leptospirosis Across Animal Species: Clinical Presentations and Organ-Specific Changes
A dog presents with fever and systemic illness, while cattle experience reproductive failure without...

Article
Psychogenic Polydipsia in Dogs: Recognising Behavioural Triggers and Clinical Indicators
A dog presents with persistent excessive drinking and urination, yet its physical examination reveal...

Article
Diagnostic Approach to Canine PU/PD: Differentiating Primary Polydipsia from Primary Polyuria
Persistent excessive drinking and urination can be the presenting signs of several conditions in dog...
.jpg)
Upcoming Event
Culture-Guided Treatment of UTIs in Dogs and Cats
Make informed antibiotic choices in canine and feline UTIs with a culture-guided approach. Explore h...

Article
Managing Psychogenic Polydipsia in Dogs: Water Intake, Behavioural Therapy and Pharmacological Intervention
Once psychogenic polydipsia (PPD) has been identified, management needs to address more than the vol...

Article
Duck Viral Hepatitis in Ducklings: Clinical Recognition and Differential Diagnosis
A sudden rise in mortality among young ducklings, particularly those under three weeks of age, shoul...

Article
Confirming Duck Viral Hepatitis: Choosing and Interpreting Diagnostic Tests
When young ducklings develop sudden mortality and liver lesions suggestive of duck viral hepatitis (...

Article
Duck Viral Hepatitis Vaccination: Managing Maternal Antibody Interference and Field Efficacy
Vaccination is a key strategy for controlling Duck Viral Hepatitis (DVH), particularly in intensive...